
Table of Contents
- The Strange Reality of Keeping an AV Fistula After Transplant
- What Happens to an AV Fistula After Kidney Transplant
- How My AV Fistula Was Created During the ESRD Crisis
- What Is an Arteriovenous Fistula (AVF)?
- Living With the AV Fistula After Kidney Transplant
- When I Realized Something Was Wrong
- Why My First Concerns Were Not Taken Seriously
- The Vascular Surgeon Consultation That Changed Everything
- Understanding AV Fistula Ligation Surgery
- My AVF Ligation Surgery Experience
- The First Two Weeks After AV Fistula Closure Surgery
- Things I Learned Too Late About AV Fistulas
- What Kidney Transplant Patients Should Monitor Long-Term
- The Psychological Meaning of Closing the AV Fistula
- When to Seek Medical Advice
- Frequently Asked Questions
- About the Author
- Medical Disclaimer
- Conclusion
The Strange Reality of Keeping an AV Fistula After Transplant
One of the least discussed parts of life after kidney transplant is what happens to the arteriovenous fistula (AVF) created during dialysis. Some fistulas remain open after transplant and cause no major problems, while others may enlarge, become symptomatic, or create vascular or cardiovascular concerns. In selected patients, an AV fistula may eventually be closed through a procedure called AVF ligation or closure.
For me, the AV fistula in my left arm remained a constant reminder of the dialysis phase even after transplant recovery had progressed. Initially, I viewed it simply as a backup plan in case dialysis was ever needed again. Many transplant patients are told exactly that. But over time, I began realizing that an active AVF is not always harmless, especially when it was created under emergency circumstances or at a less ideal location.
Nearly two years after transplant, my AV fistula gradually became a source of discomfort, anxiety, and physical symptoms I could no longer ignore. Eventually, I underwent AVF ligation surgery — a procedure that permanently closes the fistula. Looking back now, the surgery felt medically important, but emotionally symbolic too. It felt like closing one of the final remaining chapters of the dialysis years.
What Happens to an AV Fistula After Kidney Transplant
An AV fistula does not automatically have to be removed or closed after a successful kidney transplant. Some transplant recipients continue to keep their fistula open, particularly when their medical team considers it useful as potential future dialysis access.
For others, the fistula may become problematic over time. Enlargement of the veins, pain, swelling, numbness, circulation problems, or unusually high blood flow can lead to further evaluation. In selected patients, particularly when symptoms or cardiovascular concerns develop, a nephrologist and vascular surgeon may consider AV fistula ligation or closure after kidney transplant.
There is therefore no single rule that applies to every transplant recipient. The decision depends on the condition of the fistula, the patient’s vascular and cardiovascular health, the likelihood of needing dialysis again, and the assessment of the treating team.
My experience followed this less straightforward path. My fistula initially remained open after transplantation, but progressive changes eventually led to vascular surgical evaluation and, ultimately, ligation.
How My AV Fistula Was Created During the ESRD Crisis
1. The Emergency Decisions That Changed My Left Arm
When I was diagnosed with end-stage renal disease (ESRD), events moved extremely fast. My family and I were emotionally overwhelmed, frightened, and unprepared for the speed at which major medical decisions suddenly appeared.
I had studied dialysis academically years earlier as part of veterinary medicine, but becoming a dialysis patient myself was psychologically very different from understanding it theoretically. Hemodialysis began rapidly, and discussions about dialysis access happened during a period of physical weakness and emotional instability.
Like many patients entering emergency dialysis, I did not fully understand:
- long-term vascular consequences,
- fistula site selection,
- surgical strategy,
- future complications that could continue even after transplant.
That lack of understanding shaped years of consequences afterward.
2. Why My Wrist AVF Was Never Created
Ideally, many AV fistulas are first attempted near the wrist because preserving upper-arm vessels matters long-term. But in my case, repeated emergency IV lines and poor cannulation practices during hospitalization had already inflamed and damaged veins around the wrist area.
As a result, the vascular surgeon created the AV fistula near my left elbow instead.
At that time, I accepted the decision without deeply questioning its long-term implications. Looking back now, I believe several factors contributed:
- emergency circumstances,
- inadequate patient education,
- my own inexperience,
- insufficient strategic planning regarding future vascular health.
Over time, I realized that permanently losing the wrist access option was a major issue. If dialysis had ever become necessary again in the future, my vascular options would already be more limited.
I discussed some of these realities further in Hemodialysis Over Peritoneal Dialysis — What I Learned From Hemodialysis, because dialysis decisions made during a crisis can affect patients years later.
What Is an Arteriovenous Fistula (AVF)?
An arteriovenous fistula (AVF) is a surgically created connection between an artery and a vein, usually in the arm, to provide reliable vascular access for long-term hemodialysis. The increased blood flow through the vein allows blood to be removed and returned efficiently during dialysis.
AV fistulas are generally preferred for long-term hemodialysis access because they can last longer and usually have a lower infection risk than dialysis catheters. However, they can develop complications such as progressive vein enlargement, aneurysmal changes, pain, numbness, circulation problems, and, in some high-flow fistulas, increased cardiovascular workload.
These potential complications are one reason an AVF may sometimes require further assessment even after a patient has received a kidney transplant.
Living With the AV Fistula After Kidney Transplant
1. The Physical Symptoms That Slowly Started Appearing
Initially after transplant, I paid little attention to the AV fistula. My focus remained on recovery, creatinine monitoring, immunosuppressants, hydration, infection precautions, and rebuilding ordinary life.
But gradually, new symptoms began appearing in the left arm:
- bulging veins,
- visible enlargement around the fistula,
- intermittent numbness,
- heaviness in the arm,
- discomfort during activity,
- unusual sensations extending toward the lower arm and hand.

At this stage, the veins had become increasingly enlarged and uncomfortable during daily activity, especially after prolonged use of the arm.
Over time, I also began experiencing intermittent pain on the left side of my chest near the heart region, especially after using that arm more actively. The pain was not constant, but it appeared often enough to become psychologically disturbing.
What complicated matters further was uncertainty. Many transplant patients are unsure whether symptoms around old AV fistulas are dangerous, normal, temporary, or unrelated entirely.
2. The Emotional Side of Living With an Unused AV Fistula
An AV fistula after transplant is not only physical. It can become psychological too.
For me, the AV fistula represented:
- dialysis memories,
- painful needle insertions,
- fluid restriction,
- emotional exhaustion,
- dependency,
- fear of kidney failure returning again.
Even hearing the strong “thrill” vibration over the fistula could sometimes trigger subconscious anxiety linked to the dialysis period.
Many transplant patients quietly carry this psychological relationship with their old dialysis access without discussing it openly.
When I Realized Something Was Wrong
At first, I tried ignoring the symptoms because my transplant itself was functioning well. Like many transplant recipients, I became focused primarily on kidney function tests and creatinine values.
But eventually the symptoms became difficult to dismiss:
- increasing vein enlargement,
- arm discomfort,
- swelling after use,
- numbness,
- recurring chest discomfort.
One of the hardest parts was uncertainty about whether I was overthinking the symptoms or whether something medically important was actually developing.
I initially raised concerns during follow-ups, but I felt the issue was not taken as seriously as I expected. That experience itself created frustration because transplant patients often become hyperaware of bodily changes after major illness. Sometimes we fear being dismissed as anxious when symptoms are actually real.
Why My First Concerns Were Not Taken Seriously
This is an uncomfortable subject, but many patients experience it.
Once transplant function appears stable, some symptoms outside kidney lab results may receive less attention initially. Because my creatinine remained acceptable, the AV fistula concerns did not seem urgent to everyone involved.
But over time, I continued researching and monitoring the symptoms myself. I learned that large upper-arm AV fistulas can sometimes contribute to:
- high blood-flow circulation issues,
- arm swelling,
- aneurysmal vein enlargement,
- distal ischemia,
- numbness,
- cardiac strain,
- long-term vascular complications.
Eventually, I decided to seek an independent evaluation from a reputed vascular surgeon rather than continuing to wait passively.
That decision became extremely important.
The Vascular Surgeon Consultation That Changed Everything
The second vascular surgeon evaluated the AV fistula much more comprehensively.
For the first time, I received a detailed discussion regarding:
- long-term blood-flow effects,
- potential cardiac burden,
- progressive vein enlargement,
- circulation problems,
- future vascular complications if the AV fistula remained active unnecessarily.
He explained that in some transplant recipients, especially with large upper-arm AVFs, excessive blood flow may eventually create strain on the cardiovascular system. He also discussed risks of worsening vein enlargement, chronic arm symptoms, and tissue complications if progression continued.
Hearing this was emotionally difficult because I realized many of my symptoms were not imaginary after all.
After discussion between the vascular surgeon and nephrologist, AVF ligation surgery was finally planned.
Understanding AV Fistula Ligation Surgery
1. Why Some Kidney Transplant Patients Need AVF Closure
Not every kidney transplant patient needs an AV fistula removed or closed. Some AVFs remain stable for years and may be preserved as potential future dialysis access.
AVF ligation or closure may be considered when the fistula becomes symptomatic or develops clinically important complications, such as:
- High blood flow with cardiovascular effects
- Progressive vein enlargement or aneurysmal changes
- Persistent arm pain or discomfort
- Significant swelling
- Numbness or circulation problems
- Distal ischemia or steal-related symptoms
- Skin or tissue problems over enlarged veins
- Other symptoms affecting quality of life
The decision is individualized. A transplant recipient should not assume that an AV fistula must be removed simply because a kidney transplant is functioning, nor should concerning symptoms automatically be dismissed because dialysis has ended. Assessment by the nephrology and vascular surgery teams is important.
2. Possible Long-Term Risks of Leaving AVFs Open
An AV fistula that remains open after transplant may remain stable for years, but complications can develop in some patients. These may include progressive vein enlargement, aneurysmal changes, steal-related circulation problems, chronic pain, or excessive blood flow that increases cardiovascular workload.
This does not mean every functioning AVF should be closed. Rather, transplant recipients should continue paying attention to changes in the fistula and discuss new symptoms with their nephrologist or vascular surgeon
My AVF Ligation Surgery Experience
The surgery itself was emotionally significant for me.
Physically, it was a relatively smaller vascular procedure compared with transplant surgery. But psychologically, it felt much larger. I knew that closing the AV fistula meant acknowledging that the dialysis chapter had truly changed permanently.
I also understood the emotional complexity involved:
- Relief
- Uncertainty
- Fear of future kidney problems
- Hope that my transplant would continue functioning long-term
After surgery, the strong thrill sensation disappeared. That absence felt strange initially because the fistula had become physically familiar over years.
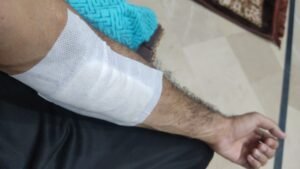
The surgical site itself remained tender and uncomfortable during the early healing phase, which I later learned is common after AVF ligation.
The First Two Weeks After AV Fistula Closure Surgery
Recovery after AV fistula removal or closure surgery is usually much smaller in scale than recovery from kidney transplantation itself, but healing can still involve swelling, tenderness, hardness around the former fistula, and gradual changes in the enlarged veins.
In my case, the most noticeable changes occurred during the first two weeks, while further vein remodeling and improvement continued over the following months. Individual recovery varies depending on the size and location of the fistula, the surgical technique, and the patient’s overall health.
1. Swelling, Hardness, and Pain Around the Closure Site
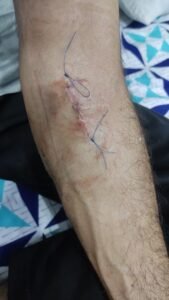
During the first several days after surgery, my left arm became swollen, hardened, and painful around the ligation site. Even touching the area caused discomfort initially.
Naturally, this triggered anxiety because transplant patients often fear complications quickly.
After discussing the recovery with my medical team and learning more about the healing process, I understood that swelling, tenderness, hardness, and changes around the former fistula can occur during recovery. Veins that have been exposed to increased blood flow for years may gradually remodel after closure, while normal postoperative inflammation and tissue healing also contribute to the early appearance of the area.
My experience should not be taken as a prediction of how another patient’s arm will heal. For me, the swelling and hardness became most noticeable during the first week, then gradually started decreasing after around six days.
2. The Fear of Something Going Wrong
One important reality many medical articles ignore is the psychological side of post-surgical recovery.
After major medical experiences like dialysis and transplant, patients often become hypervigilant about bodily symptoms. Every swelling, sensation, or discomfort can trigger fear.
I monitored:
- arm color,
- temperature,
- wound appearance,
- swelling progression,
- circulation repeatedly.
That anxiety is extremely common after years of medical trauma.
I was also prescribed antibiotics after surgery, which helped reduce infection concerns during early healing.
3. Gradual Improvement and Vein Remodeling
By around two weeks, the situation improved significantly. My sutures were removed, swelling had reduced considerably, and the arm gradually began feeling more normal.
However, healing did not end completely at that point.
Over the following months:
- veins slowly remodeled,
- enlargement reduced progressively,
- arm heaviness improved,
- I carefully avoided heavy lifting using that arm.
I intentionally used the arm lightly during recovery because I wanted healing to progress gradually without unnecessary strain.
One reassuring realization was that the disturbing chest discomfort episodes also improved substantially after AVF ligation.
Things I Learned Too Late About AV Fistulas
Looking back now, several lessons became very clear to me:
- vascular access decisions matter enormously,
- fistula site selection should be strategic,
- preserving wrist vessels matters,
- surgeon experience matters greatly,
- patients should ask more questions,
- long-term complications deserve serious attention.
I also learned that transplant success does not automatically erase all consequences from the dialysis period. Some effects continue physically and psychologically for years.
This experience strengthened my belief that patients need earlier and more balanced education regarding dialysis access planning. I explored many of these concerns further in Dialysis Before Transplant: What It Really Feels Like and Hemodialysis Over Peritoneal Dialysis — What I Learned From Hemodialysis.
What Kidney Transplant Patients Should Monitor Long-Term
Transplant recipients with AV fistulas should continue monitoring:
- Rapid vein enlargement
- Pain
- Numbness
- Swelling
- Hand coldness
- Skin color changes
- Reduced circulation
- Chest pain or unusual shortness of breath
- Arm weakness
- Worsening cosmetic distortion
Do not ignore symptoms simply because transplant labs appear stable.
The Psychological Meaning of Closing the AV Fistula
For me, AVF ligation symbolized:
- closure of the dialysis phase,
- release from a physical reminder of dependency,
- gradual emotional movement toward a different chapter of life.
At the same time, it also reminded me how deeply kidney disease changes a person psychologically. Even after successful transplant, traces of dialysis remain in the body, routines, and mind.
When to Seek Medical Advice
Seek immediate medical advice for:
- severe swelling
- bleeding
- redness or discharge from the surgical site
- fever,
- worsening numbness
- hand discoloration
- shortness of breath
Kidney transplant recipients with AV fistulas should continue periodic vascular assessment if symptoms develop, even years after transplant.
Frequently Asked Questions
What happens to an AV fistula after kidney transplant?
An AV fistula does not automatically need to be removed after a successful kidney transplant. Some remain open as potential future dialysis access, while others may eventually be closed if they develop significant symptoms or complications. The decision depends on the individual patient’s vascular and cardiovascular situation.
Does an AV fistula need to be removed after kidney transplant?
No. Not every AV fistula needs removal or closure after transplant. Some remain stable without causing problems. Closure may be considered when an AVF becomes symptomatic, has problematic blood flow, develops significant enlargement, or creates other vascular or cardiovascular concerns.
Can an AV fistula cause heart problems?
Large, high-flow AV fistulas can increase cardiovascular workload in some patients. The significance varies between individuals, so suspected high-flow problems should be assessed by the treating medical team.
Is AV fistula closure the same as AV fistula removal?
AV fistula closure is commonly called ligation. The procedure closes the abnormal artery-to-vein connection rather than simply “removing” the entire arm vein. The exact surgical approach depends on the anatomy and the reason for closure.
Is swelling after AV fistula closure normal?
Swelling, tenderness, hardness, and gradual changes around the former fistula can occur during early healing. However, worsening swelling, bleeding, fever, wound discharge, severe pain, hand discoloration, worsening numbness, chest pain, or shortness of breath require prompt medical assessment.
How long does recovery after AV fistula closure surgery take?
Early healing may occur over the first few weeks, while deeper tissue and vein remodeling can continue for several months. Recovery varies according to the fistula, surgical procedure, and individual health.
About the Author
Dr. Salman is a veterinarian (DVM, M.Phil.) and kidney transplant recipient who underwent transplant surgery in August 2023. Through Renal Renewal, he writes about dialysis realities, transplant recovery, immunosuppressant management, mental health, hydration, and long-term graft care using lived experience combined with medically responsible education. He is not a human medical doctor or nephrologist.
Medical Disclaimer
This article is based on personal experience and educational information and should not replace professional medical advice, diagnosis, or treatment. AV fistula management decisions are individualized and should always be discussed with qualified nephrologists and vascular surgeons familiar with your medical condition.
Conclusion
Closing my AV fistula was medically important, but emotionally it also represented the gradual closing of one of the hardest periods of my life. The fistula had once kept me alive during kidney failure, yet over time it also became a source of physical symptoms, psychological burden, and long-term vascular complications I could no longer ignore.
Looking back now, I understand how many dialysis-related decisions are made during moments of fear, urgency, and limited patient understanding. That is why long-term thinking matters so much. Vascular access planning, surgeon selection, dialysis education, and post-transplant monitoring all carry consequences that may continue years beyond dialysis itself.
For transplant patients still living with active AV fistulas, the goal is not fear but awareness. Symptoms should not be dismissed automatically, and patients deserve thoughtful evaluation when concerns develop. Recovery after transplant is rarely only about kidney numbers. It is also about rebuilding physical stability, emotional confidence, and trust in your own body again over time.